A53T alpha-synuclein transgenic mice express a mutant human SNCA transgene and are used to study the resulting proteinopathy and motor phenotype. This article focuses on line M83, the evidence supporting its phenotype, the endpoints a sponsor can specify, and the distinction from induced preformed-fibril models.[S1][S2][S4]
What the M83 model is
A familial Parkinson disease study identified a mutation in the alpha-synuclein gene in affected kindreds.[S3] The later M83 model expresses human A53T alpha-synuclein under the Prnp promoter; its formal strain designation is B6;C3-Tg(Prnp-SNCA*A53T)83Vle/J.[S1][S2]
The founding study reported age-dependent severe motor impairment, paralysis, death, and intracellular alpha-synuclein-positive inclusions in mice expressing the A53T mutant, while mice expressing wild-type human alpha-synuclein did not develop the same severe motor phenotype.[S1] These findings define the model phenotype; they do not mean the mouse reproduces every feature of Parkinson disease or predicts a patient response.
Questions the model can address
Study question
What M83 can establish
Mutant alpha-synuclein proteinopathy
The location, biochemical fraction, and time course of transgene-associated alpha-synuclein accumulation and inclusions[S1]
Motor phenotype
Onset and progression of motor impairment, paralysis, and survival within the specified colony[S1]
Mechanism-based pharmacology
Whether an intervention changes prespecified biochemical, histologic, or motor endpoints in M83 mice
Use the model when the study question depends on mutant alpha-synuclein expression, inclusion pathology, or the associated motor decline. If the question instead concerns seeded propagation from a defined anatomical site, an inoculated preformed-fibril model represents a different experiment.[S1][S4]
Endpoint group
Commissioning considerations
Alpha-synuclein pathology
Define soluble and insoluble fractions, antibody specificity, regions sampled, inclusion-scoring rules, and whether pSer129 is primary or supportive.
Motor function and clinical observations
Select rotarod, pole, grip-strength, gait, or observation measures in advance; separate motor decline from general condition and terminal disease.
Neuroinflammation and synaptic markers
Predefine regions and quantitative image-analysis methods for Iba1, GFAP, or synaptic markers; treat them as model readouts rather than evidence of human neuroprotection.
Pharmacology
Link the proposed mechanism to a primary biochemical, histologic, or functional endpoint and include exposure confirmation.
Foundational M83 evidence
Phenotype reported in A53T-expressing mice
The 2002 study generated mice expressing human wild-type or A53T alpha-synuclein in central nervous system neurons. Mice expressing the mutant protein developed severe motor impairment that resulted in paralysis and death, whereas the wild-type-expressing comparison did not develop that severe phenotype. The study also reported neuronal alpha-synuclein inclusions.[S1] This comparison supports an A53T-associated phenotype in that transgenic system; it is not proof of the complete causal sequence of human neurodegeneration.
Model identity and sourcing
Search rank is not a model-selection criterion. Confirm the formal strain designation, stock identifier, promoter, transgene, background, zygosity, colony age distribution, and expected phenotype before comparing study proposals.
M83 strain record
The verified US strain record lists M83 as B6;C3-Tg(Prnp-SNCA*A53T)83Vle/J, Stock No. 004479. It expresses human A53T alpha-synuclein under the Prnp promoter and derives from the 2002 transgenic study.[S1][S2]
Before commissioning an M83 study, confirm the strain and stock identifier, breeding and zygosity, age-dependent phenotype in the working colony, survival and humane-endpoint plan, target-tissue exposure, and a primary endpoint linked to the proposed mechanism.[S2] If seeded propagation is the question, specify a PFF design instead of assuming that M83 answers it.[S4]
3 Recommended Contract Research Organizations
for Non-Clinical Studies
— by Target goal and Expertise
In non-clinical development, the choice of contract research organization shapes the quality of the data and the time it takes to reach the next decision. Below, three CROs are introduced by the type of study they support: pharmacology (efficacy) studies, safety studies, and pharmacokinetic (PK/PD) studies. Each summary describes the services the company offers so that you can match a provider to your target and development objective.
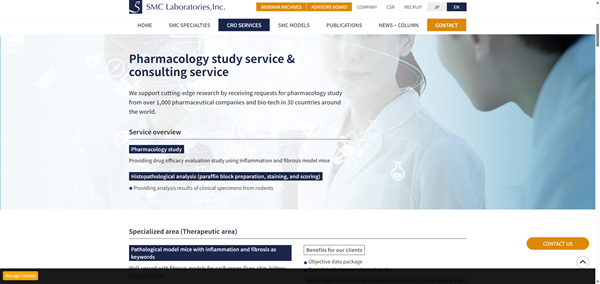
Pharmacology (Efficacy) StudiesDisease-Relevant Models for Translational Drug Evaluation
Reference: SMC Laboratories, Inc. official website (https://www.smccro-lab.com/)
SMC Laboratories, Inc.
SMC Laboratories is a specialized non-clinical CRO focused on in vivo pharmacology and efficacy studies using disease-relevant animal models, particularly in fibrosis, inflammation, metabolic diseases, and oncology.
Areas of Expertise
Disease-Relevant Model Portfolio
SMC Laboratories offers models covering the liver, lung, kidney, intestine, and oncology. Its portfolio includes the proprietary STAM™ model for MASH, fibrosis, and hepatocellular carcinoma.
Study Design Based on Target Biology
Study plans are developed around the target biology, mechanism of action, disease stage, and development objective. Pharmacological endpoints can be combined with histopathology, biomarkers, and disease-specific readouts.
Support from Target Validation to Proof of Concept
With experience from more than 1,000 studies for clients in 30 countries, SMC Laboratories supports programs from target validation and candidate selection through in vivo proof-of-concept studies.
Safety StudiesComprehensive Safety Assessment for Preclinical Development
Reference: Charles River Laboratories official website (https://www.criver.com/)
Charles River Laboratories
Charles River provides non-clinical toxicology and safety assessment services for programs ranging from exploratory safety studies to IND-enabling development.
Areas of Expertise
General Toxicology Across Study Designs
Services include single- and repeat-dose toxicology, dose-range finding, and general toxicology studies across multiple species and administration routes.
Non-GLP and GLP Study Support
Charles River supports both non-GLP and GLP studies, allowing sponsors to progress from early safety characterization to studies intended for regulatory submissions.
Integrated IND-Enabling Safety Assessment
Toxicology studies can be integrated with toxicokinetics, clinical pathology, histopathology, and safety pharmacology to support interpretation and IND-enabling safety packages.
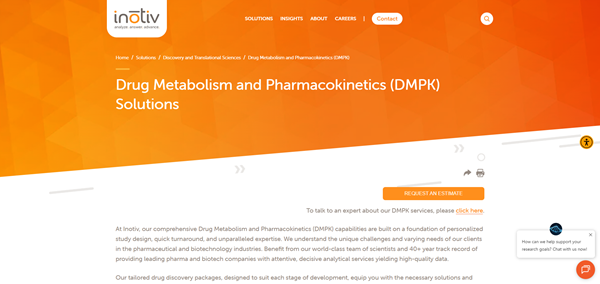
Pharmacokinetic (PK/PD) StudiesConnecting Drug Exposure with Pharmacological Response
Reference: Inotiv official website (https://www.inotiv.com/)
Inotiv
Inotiv provides integrated PK/PD, DMPK, and bioanalytical services to characterize drug exposure and its relationship with pharmacological response.
Areas of Expertise
Pharmacokinetic Characterization
PK studies characterize exposure, half-life, clearance, and other pharmacokinetic parameters needed to understand how a candidate behaves in the selected model.
Exposure–Response Evaluation
Pharmacokinetic data can be combined with pharmacodynamic endpoints and bioanalysis to evaluate the relationship between drug exposure and pharmacological response.
Integrated DMPK and Development Support
Integrated DMPK, pharmacology, and safety information supports candidate comparison, dose selection, dosing-frequency optimization, and decisions about subsequent preclinical development.

 Japanese