Success rates in drug development, and where programs stop
Attrition figures for drug development are quoted in several forms, and they are not comparable unless the denominator is stated. Counting from compound screening produces a very large ratio, because it includes every molecule ever tested. Counting from the start of clinical trials produces a percentage. This article uses the second, because it is the figure published sources support: the Congressional Budget Office reports that only about 12 percent of drugs entering clinical trials are ultimately approved,[S2] and an analysis of more than 400,000 trials covering 21,143 compounds puts the overall probability of reaching approval at 13.8 percent.[S1]
What follows covers the transition rates between clinical phases, why the largest single loss occurs in phase 2, and what that implies for how nonclinical studies are designed.
Transition rates by phase
The figures below are the probabilities of moving from one phase to the next, taken from a published analysis of 406,038 clinical trials conducted between January 2000 and October 2015.[S1] They differ from figures quoted elsewhere because the sample and the period differ; the source is given so the basis can be checked.
Overall, from entering clinical trials to approval
13.8%[S1], or about 12% by a separate estimate[S2]
Why phase 2 loses the most
Phase 2 has the lowest transition probability of the three.[S1] It is also the first phase in which efficacy is tested in patients with the disease, which is why it is where the difference between an animal result and a human result becomes visible. This difference is usually called the translational gap: a compound produced a clear effect in a disease model and does not produce one in patients. For a nonclinical programme this is the failure that matters, because it is the one the earlier work was supposed to anticipate.
What programs stop for
The distribution of reasons for stopping has shifted over the decades. Failures caused by poor pharmacokinetics, meaning a compound that was not absorbed, did not reach the target tissue, or was cleared too quickly, were once a dominant cause and are now much less common, because those properties are screened for early and measured well. Efficacy is the reason that has not moved. A compound that is absorbed, reaches its target and is well tolerated can still fail to change the disease.
The translational gap
Efficacy failure means the treatment effect expected from the nonclinical work did not appear in patients. Four differences between an animal model and a patient account for most of it, and each has a different implication for study design. They are described below. None of them is a reason to skip animal work; they are reasons to be specific about what a given model can and cannot show.
The target differs between species. A receptor or signalling protein that differs by a small number of amino acids between the animal and the human can bind a compound with materially different affinity. An inhibitor that is potent against the rodent target may be substantially weaker against the human one, and the animal efficacy result then says little about the human dose. Where the target sequence differs, binding affinity against the human protein should be measured directly rather than inferred.
Metabolism differs between species. If the activity observed in an animal comes largely from a metabolite, and that metabolite is formed in humans at much lower levels or not at all, the effect will not carry over. Drug-metabolizing enzyme activity and the routes themselves differ between species. This is the argument for characterizing metabolite profiles across species early rather than treating metabolism purely as a safety question.
The model is usually acute and the disease is usually chronic. Most models induce a lesion over weeks by diet, an agent or a genetic change, while the human disease develops over years alongside other conditions. A short-duration model may not reproduce the tissue state a drug has to penetrate in an advanced patient, nor the signalling that accumulates over a long course. This is a limitation of the design rather than a defect in a particular model, and it is the reason model choice should follow from which stage of the disease the drug is meant to act on.
The immune system of a laboratory animal is not the immune system of a patient. Animals are housed under defined health status, with limited and uniform environmental exposure, while patients vary widely in immune history. For diseases in which chronic inflammation drives the pathology, that difference changes what an efficacy result means. This article does not rank the four differences; the original text described this one as the largest contributor to phase 2 efficacy failure, and no source for that ordering could be located.
What follows from this for study design is narrower than it is sometimes made to sound. Ask whether the model reproduces the stage of disease the drug is meant to act on, not merely the disease name. Ask what the historical control data for that model look like at the laboratory that will run it, since variability in the model sets the effect size the study can detect. Ask whether affinity against the human target has been measured. And where a human cell system can answer a species-difference question that an animal cannot, run it, without treating it as a substitute for the animal work that a regulatory submission requires.[S3]
References
Wong CH, Siah KW, Lo AW. Estimation of clinical trial success rates and related parameters. Biostatistics. 2019;20(2):273-286 (PMID 29394327; PMCID PMC6409418; DOI 10.1093/biostatistics/kxx069). https://doi.org/10.1093/biostatistics/kxx069 (accessed 2026-09-03)
Congressional Budget Office — Research and Development in the Pharmaceutical Industry, April 2021. https://www.cbo.gov/publication/57126 (accessed 2026-09-03)
3 Recommended Contract Research Organizations
for Non-Clinical Studies
— by Target goal and Expertise
In non-clinical development, the choice of contract research organization shapes the quality of the data and the time it takes to reach the next decision. Below, three CROs are introduced by the type of study they support: pharmacology (efficacy) studies, safety studies, and pharmacokinetic (PK/PD) studies. Each summary describes the services the company offers so that you can match a provider to your target and development objective.
Pharmacology (Efficacy) StudiesDisease-Relevant Models for Translational Drug Evaluation
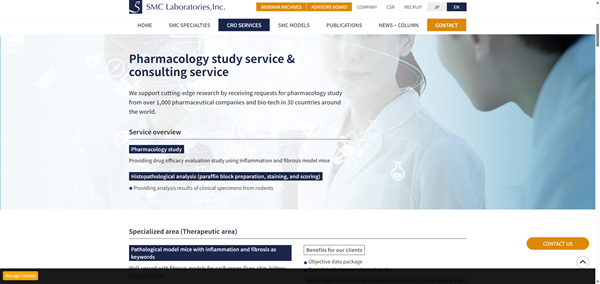
Reference: SMC Laboratories, Inc. official website (https://www.smccro-lab.com/)
SMC Laboratories, Inc.
SMC Laboratories is a specialized non-clinical CRO focused on in vivo pharmacology and efficacy studies using disease-relevant animal models, particularly in fibrosis, inflammation, metabolic diseases, and oncology.
Areas of Expertise
Disease-Relevant Model Portfolio
SMC Laboratories offers models covering the liver, lung, kidney, intestine, and oncology. Its portfolio includes the proprietary STAM™ model for MASH, fibrosis, and hepatocellular carcinoma.
Study Design Based on Target Biology
Study plans are developed around the target biology, mechanism of action, disease stage, and development objective. Pharmacological endpoints can be combined with histopathology, biomarkers, and disease-specific readouts.
Support from Target Validation to Proof of Concept
With experience from more than 1,000 studies for clients in 30 countries, SMC Laboratories supports programs from target validation and candidate selection through in vivo proof-of-concept studies.
Safety StudiesComprehensive Safety Assessment for Preclinical Development
Reference: Charles River Laboratories official website (https://www.criver.com/)
Charles River Laboratories
Charles River provides non-clinical toxicology and safety assessment services for programs ranging from exploratory safety studies to IND-enabling development.
Areas of Expertise
General Toxicology Across Study Designs
Services include single- and repeat-dose toxicology, dose-range finding, and general toxicology studies across multiple species and administration routes.
Non-GLP and GLP Study Support
Charles River supports both non-GLP and GLP studies, allowing sponsors to progress from early safety characterization to studies intended for regulatory submissions.
Integrated IND-Enabling Safety Assessment
Toxicology studies can be integrated with toxicokinetics, clinical pathology, histopathology, and safety pharmacology to support interpretation and IND-enabling safety packages.
Pharmacokinetic (PK/PD) StudiesConnecting Drug Exposure with Pharmacological Response
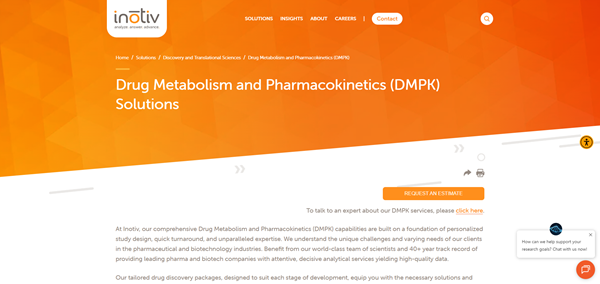
Reference: Inotiv official website (https://www.inotiv.com/)
Inotiv
Inotiv provides integrated PK/PD, DMPK, and bioanalytical services to characterize drug exposure and its relationship with pharmacological response.
Areas of Expertise
Pharmacokinetic Characterization
PK studies characterize exposure, half-life, clearance, and other pharmacokinetic parameters needed to understand how a candidate behaves in the selected model.
Exposure–Response Evaluation
Pharmacokinetic data can be combined with pharmacodynamic endpoints and bioanalysis to evaluate the relationship between drug exposure and pharmacological response.
Integrated DMPK and Development Support
Integrated DMPK, pharmacology, and safety information supports candidate comparison, dose selection, dosing-frequency optimization, and decisions about subsequent preclinical development.

 Japanese