A disease model is an animal in which a condition resembling a human disease has been induced or is present genetically, so that a candidate can be tested against something other than a healthy animal. What the model reproduces is a set of measurable features of the disease, not the disease itself. When a sponsor is choosing where to place efficacy work, whether the laboratory runs the specific model the programme needs is usually the deciding factor, because establishing a model that a laboratory has not run before adds months and introduces variability that is hard to separate from a treatment effect.
What a model result establishes
An efficacy study in a disease model establishes that the candidate changed a measured feature of that model, at a stated exposure, relative to a control group. That is the whole of what it establishes. It is enough to support a decision about whether to continue, which is why these studies are run before the regulated safety package.[S3] It is not a measurement of efficacy in patients, and a result in a model does not predict a clinical outcome.
Animal models and human cell-based systems
Systems built from human induced pluripotent stem cells address one specific limitation of animal models: the species difference in the target and in the pathways around it. Because the cells are human, a compound is tested against human protein sequences, which an animal model cannot provide. What such a system cannot provide is the whole organism, so it does not replace the animal study and it does not answer questions about distribution, metabolism or systemic effects. This article makes no claim that these systems reduce the rate at which programmes are stopped; no source establishing that could be located.
Choosing a model
The model has to contain the mechanism the drug is meant to act on, which is a narrower requirement than sharing the disease name. A compound intended to reverse fibrosis needs a model in which fibrosis is established, not one in which it is still developing. A compound acting on an immune pathway needs a model in which that pathway drives the pathology. Selection conventions exist by disease area, such as strains that develop hypertension spontaneously for cardiovascular work, and they are a starting point rather than an answer. Programmes typically begin in rodents and move to rabbits, dogs, non-human primates, pigs or goats where the question requires a larger animal, most often for anatomical reasons or for the volume of sample needed.
Four things are worth establishing with the laboratory before the model is agreed. What the historical control data look like for that model at that site, since the variability in the model determines the effect size the study can detect. How the model is confirmed to have taken, and what happens to animals in which it has not. At what point after induction the readout is taken, and why that timepoint. And how many times the laboratory has run it, since a model established for the first time on a sponsor study carries the setup variability as well as the treatment question.
Humanized animals sit between the two. In one approach human cells or tissue are engrafted into an immunodeficient animal and allowed to establish; in another, a segment of the animal genome is replaced with the human sequence. Both narrow a specific species difference rather than removing species differences generally, and both introduce their own constraints, since an animal that accepts a human graft is by definition immunodeficient. The question to ask of any humanized model is which human component it actually contains, because that determines what the result can be read to mean.
3 Recommended Contract Research Organizations
for Non-Clinical Studies
— by Target goal and Expertise
In non-clinical development, the choice of contract research organization shapes the quality of the data and the time it takes to reach the next decision. Below, three CROs are introduced by the type of study they support: pharmacology (efficacy) studies, safety studies, and pharmacokinetic (PK/PD) studies. Each summary describes the services the company offers so that you can match a provider to your target and development objective.
Pharmacology (Efficacy) StudiesDisease-Relevant Models for Translational Drug Evaluation
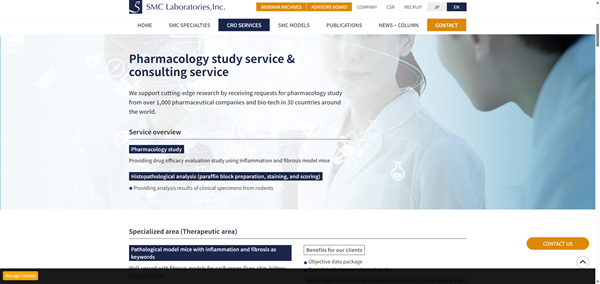
Reference: SMC Laboratories, Inc. official website (https://www.smccro-lab.com/)
SMC Laboratories, Inc.
SMC Laboratories is a specialized non-clinical CRO focused on in vivo pharmacology and efficacy studies using disease-relevant animal models, particularly in fibrosis, inflammation, metabolic diseases, and oncology.
Areas of Expertise
Disease-Relevant Model Portfolio
SMC Laboratories offers models covering the liver, lung, kidney, intestine, and oncology. Its portfolio includes the proprietary STAM™ model for MASH, fibrosis, and hepatocellular carcinoma.
Study Design Based on Target Biology
Study plans are developed around the target biology, mechanism of action, disease stage, and development objective. Pharmacological endpoints can be combined with histopathology, biomarkers, and disease-specific readouts.
Support from Target Validation to Proof of Concept
With experience from more than 1,000 studies for clients in 30 countries, SMC Laboratories supports programs from target validation and candidate selection through in vivo proof-of-concept studies.
Safety StudiesComprehensive Safety Assessment for Preclinical Development
Reference: Charles River Laboratories official website (https://www.criver.com/)
Charles River Laboratories
Charles River provides non-clinical toxicology and safety assessment services for programs ranging from exploratory safety studies to IND-enabling development.
Areas of Expertise
General Toxicology Across Study Designs
Services include single- and repeat-dose toxicology, dose-range finding, and general toxicology studies across multiple species and administration routes.
Non-GLP and GLP Study Support
Charles River supports both non-GLP and GLP studies, allowing sponsors to progress from early safety characterization to studies intended for regulatory submissions.
Integrated IND-Enabling Safety Assessment
Toxicology studies can be integrated with toxicokinetics, clinical pathology, histopathology, and safety pharmacology to support interpretation and IND-enabling safety packages.
Pharmacokinetic (PK/PD) StudiesConnecting Drug Exposure with Pharmacological Response
Reference: Inotiv official website (https://www.inotiv.com/)
Inotiv
Inotiv provides integrated PK/PD, DMPK, and bioanalytical services to characterize drug exposure and its relationship with pharmacological response.
Areas of Expertise
Pharmacokinetic Characterization
PK studies characterize exposure, half-life, clearance, and other pharmacokinetic parameters needed to understand how a candidate behaves in the selected model.
Exposure–Response Evaluation
Pharmacokinetic data can be combined with pharmacodynamic endpoints and bioanalysis to evaluate the relationship between drug exposure and pharmacological response.
Integrated DMPK and Development Support
Integrated DMPK, pharmacology, and safety information supports candidate comparison, dose selection, dosing-frequency optimization, and decisions about subsequent preclinical development.

 Japanese